- Home
- IPK
intractable plantar keratoma
• An intractable plantar keratoma (IPK) is a painful, deep‑seated callus that forms under a metatarsal head due to excessive pressure and shearing forces. It often feels like “a stone in the shoe” and hurts more on hard floors or in thin‑soled or high‑heeled shoes.
• IPKs develop when a callus undergoes cystic degeneration at its center, creating a hard core that becomes significantly more painful than the surrounding skin. This occurs where shearing forces intersect beneath the ball of the foot during walking.
• Structural foot issues commonly contribute, including elongated or plantarflexed metatarsals, a short or hypermobile first metatarsal, enlarged condyles, rigid hammertoes, or loss of natural fat padding under the ball of the foot. These abnormalities increase localized pressure and make IPKs more likely.
• Conservative care includes wearing lower‑heeled, cushioned shoes; avoiding thin soles; using pads or cushions; and having a podiatrist regularly trim and debride the lesion. Orthotics can redistribute pressure and significantly reduce recurrence when the cause is biomechanical.
• Surgical options exist for severe, unresponsive cases but have mixed success. Procedures may include elevating or shortening a metatarsal (osteotomy) or shaving an enlarged condyle. Risks include over‑correction, transfer lesions, and non‑union of bone.
Reviewed by: Medical Review Board
WHAT IS AN INTRACTABLE PLANTAR KERATOMA
Ok, here is the situation. All of a sudden you have noticed this pain on the ball of your foot. Additionally, you also noticed this “hard spot” in the same location. Prior to this you may have had the “hard spot” or callus and although you knew it was there it did not really bother you. Now, however, the area really hurts.
Many people will complain that it feels like they have a stone in their shoe; the problem is, the “stone” is there all the time. It will hurt more if you are walking barefoot on a hard floor, it will feel better on a carpeted floor. It will hurt if you are wearing a thin soled shoe, or a high heel; it will feel somewhat better if you are in sneakers. You may have even tried to trim it away or put a pad on it to make it feel somewhat better, but ultimately it just hurts. So what is it?
The most common cause for this scenario is what is known as an intractable plantar keratoma or commonly referred to as an IPK. This is a benign condition that develops as a result of cystic degeneration in a callused area. In simpler terms, there is excessive pressure under one of the metatarsal heads. The pressure itself will initially cause a callus to form. The callus itself may or may not be a painful condition; some require treatment, many do not. This will result from excessive shearing forces occurring in the center of the callus.
|
WHAT CAUSES AN INTRACTABLE PLANTAR KERATOMA
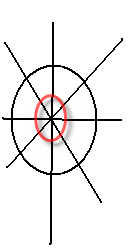
In the diagram shown here the larger black circle represents the callus that you might have. All the straight lines represent the shearing forces that are occurring as you walk. What generally causes shearing forces is the pivoting on the metatarsal head as you walk. The point where all the shearing forces cross each other causes the skin to undergo cystic changes and thus this area becomes harder than the surrounding callus and a lot more painful (red circle). This is your IPK.
SPECIFIC CAUSES OF INTRACTABLE PLANTAR KERATOMA DUE TO FOOT STRUCTURE
The formation of this cystic lesion can be caused by a number of structural problems in the foot.
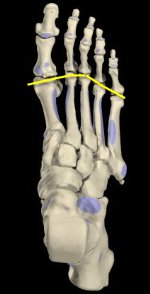
Elongated metatarsal head. Looking at the diagram, a ‘normal’ foot structure results in the formation of a parabola (arc), represented by the yellow line, where generally the second metatarsal head is the longest.
|
In situations where there is a distortion of the parabola such as an excessively long third metatarsal head, or even a second metatarsal head, a callus may eventually form underneath the bone and ultimately then a intractable plantar keratoma.
Excessively short first metatarsal head. In the case of the second metatarsal head the condition can be exacerbated by problems under the first metatarsal head. Either the first metatatarsal head is excessively short thus putting more pressure under the second metatarsal head, or the
First metatarsal head may be hypermobile. The first metatarsal head, more so than the other metatarsal heads, has the ability to move up and down during the gait cycle. In foot deformities where the head moves upward too much (hypermobile), it puts excessive pressure on the second metatarsal head and opens the door for an intractable plantar keratoma.
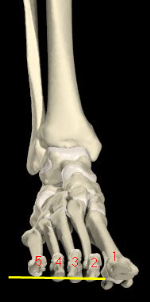
Plantarflexed metatarsal. Another situation that will cause an intractable plantar keratoma is the weightbearing capability of each metatarsal relative to each other. In theory, the lesser metatarsals (2-5) should each bear equal weight during the gait cycle. However, some people have a variation in the metatarsal heads and one metatarsal head may be more plantarflexed (bent downward) than the other metatarsal heads and so that particular metatarsal head will bear more weight and thus be more prone to formation of an intractable plantar keratoma.
|
Looking at the diagram, if the horizontal yellow line represents the walking surface you can see that the third metatarsal head is below the yellow line meaning that it is subject to much more pressure than the adjacent metatarsal heads and so it will be more prone to forming an intractable plantar keratoma.
Shape of the metatarsal head. Along this line of thought is the idea that the shape of a given metatarsal head may also precipitate the formation of an intractable plantar keratoma . The underside of each metatarsal head consists of two condyles, which are rounded protrusions of bone. In some individuals the lateral condyle (the one on the outside) will be excessively large and this can contribute to the formation of an intractable plantar keratoma.
Hammertoes. Also to be considered are the effects of hammertoes , particularly what are known as rigid hammertoes. As the name implies, these are toes that stay bent or crooked during weightbearing and non-weightbearing. The excessively bent toe puts a retrograde or downward pressure on the metatarsal head just behind it, thus creating more pressure against the ground. This can contribute to the formation of an intractable plantar keratoma.
Lack of fat on ball of foot. Other anatomical considerations include the amount of fat that an individual has under the ball of their foot. The one part of the body where we do need to be fat is the bottom of the foot, unfortunately, the one part of the body where we lose fat as we age is the ball of the foot. Without the added cushioning, some people will be more prone to intractable plantar keratoma formation. I should also mention that conditions like rheumatoid arthritis will also exacerbate the formation of an IPK.
Common conditions that may mimic an intractable plantar keratoma is a plantar wart and a porokeratosis. If you go to your family doctor complaining of a painful growth on the bottom of the foot, more often than not, you will get a diagnosis of wart. In all fairness, warts can “grow” in callused areas of the foot, but the majority of these lesions are intractable plantar keratoma.
TREATMENT OF INTRACTABLE PLANTAR KERATOMA
conservative care
Shoe selection. How do we go about treating this condition? In many instances changing the type of shoe that you wear will actually eliminate the problem. For example, the higher the heel that you wear, the more pressure you put on the ball of the foot. Wear lower heels. Very thin soled shoes will aggravate the condition; try wearing thicker soled shoes with a more cushioned bottom. Many of you will notice that the problem hurts much less when in sneakers compared to high style dress shoes.
Pads and cushions. Many people will resort to buying different types of pads to cushion the area and yes that can help. A few words of caution. If you are using adhesive pads, they should be changed daily. If not you run the risk of developing an infection under the pad or perhaps have an allergic reaction to the adhesive in the pad. Be careful when removing the pads, you do not want to tear the skin otherwise the foot will hurt more.
Avoid using medicated pads especially if you are diabetic or have poor circulation. Medicated pads contain an acid. The idea is for the acid to eat away at the IPK to make it feel more comfortable. The problem with acid, is that it does not know when to stop, so it will eat right through the IPK into healthy skin and you run the risk of creating a skin ulcer. Again, those who are diabetic or suffer from poor circulation are more at risk, but why would anyone want to continuously create this type of problem?
Professional medical care. Other treatment options include visiting a podiatrist periodically who will trim the callus and curette (carve out) the intractable plantar keratoma. This is generally not a permanent cure and has to be repeated periodically, but having said that, I can also tell you that over the years I have had a number of patients who had very painful IPK’s that gradually disappeared or reduced in size due to nothing more than regular professional care.
Orthotics. When the intractable plantar keratoma is due to a biomechanical problem such as an elongated metatarsal bone, or excessively hypermobile first metatarsal bone, an orthotic can be very helpful. Depending on the underlying cause, a custom orthotic can be built to take pressure off the IPK.
This is accomplished either by adding a metatarsal pad behind the growth and thus reducing pressure on the IPK as the foot rolls forward or by the use of an accommodative padding which is essentially a pad that covers the whole forefoot with the exception of the IPK. Here the pad is cut out which basically allows the affected metatarsal head to "float" or reduce the direct ground pressure against the metatarsal head and reduce pressure on the growth. With either type of padding what generally happens is either the growth disappears over time, or the time it takes for the growth to come back is dramatically increased.
surgery
There are surgical approaches for the treatment of intractable plantar keratoma in those individuals where nothing else gives satisfactory relief. The problem here is that the success rate is not a high as it is for other foot procedures.
One surgical approach is to take the plantarflexed metatarsal, perform an osteotomy (surgical breaking of bone) and “raise” the metatarsal head to be in better alignment with the adjacent metatarsal heads and in theory that should eliminate the IPK. When successful, it does eliminate the IPK, but there are two major problems here.
One is over correcting the elevation and thus creating more pressure on the metatarsal bones next to it and ultimately the formation of an intractable plantar keratoma on one of those bones.
The other problem is that of a non-union of the osteotomy, where the surgical breaking of bone does not heal. This problem will tend to be more prevalent in procedures that look to shorten the offending the metatarsal bone to improve the parabola. In these cases, a portion of bone has to be removed in an effort to shorten the bone.
If it is determined that the problem is due to an enlarged condyle, a simple condylectomy (shaving of the condyle) may be indicated. This is a simpler procedure than an osteotomy and there is no worry of a non-union. The issue here has to do with which metatarsal head requires the condylectomy; some are easier to reach surgically than others. We generally try to avoid incisions on the bottom of the foot, so to get to the bottom of the foot, we have to make the incisions on top of the foot which as you can imagine can be difficult.
In summary, an intractable plantar keratoma is a condition that generally responds quite well to conservative care, in many cases just a change in shoe selection. Always try the simplest things first. If you cannot get the relief you are trying to achieve through conservative means, then discuss more invasive options with your doctor.
Frequently Asked Questions
REFERENCES
If you happen to live in the New York - New Jersey area and would like to visit our office
|
|
To make an appointment online or for directions to our office click Dr. Marc Mitnick.
DISCLAIMER: The purpose of this site is purely informational in nature. It is not intended to diagnose, treat or cure any medical condition. This information is not a substitute for advice from a medical professional. Please consult your healthcare provider for accurate diagnosis and treatment. The information presented here may be subject to errors and omissions.
SITE LAST UPDATED: October 2026

Recent Articles


-
Vitamin D impact on health
Feb 06, 23 07:17 PM
Researchers are suggesting that the effectiveness of Vitamin D in fighting and preventing disease is predicated on a persons body mass index (BMI). The thinner the person the greater the positive impa… -
Foods to speed up healing
Feb 01, 23 02:41 PM
One of the best ways to help yourself heal faster after surgery is to eat well. Getting the proper nutrition will provide your body with the essentials it needs to promote healing. Here is a suggestio… -
Cancer and Type 2 Diabetes
Jan 25, 23 04:52 PM
An article revealing that older type 2 diabetics have a higher incidence of cancer then non-diabetics. It is suggested that cancer may surpass CVD as the number one cause of death in older diabetics. -
Does glucosamine or MSM reduce arthritis pain?
Jan 22, 23 01:41 PM
A good review of the possible benefits to taking glucosamine, chondroitin or MSM for arthritis. Always beware of the possible side effects of over the counter supplements. -
shin splints
Jan 18, 23 05:12 PM
A great review on the various causes of shin splints, along with treatment options. -
Whats new in skin cancer?
Jan 15, 23 08:32 PM
A presentation of newer skin protection combinations in an effort to better protect the skin from the hazards of sun exposure. -
Causes and risk factors of warts
Jan 14, 23 05:02 PM
A good review of the causes of warts and protective measures you can take to prevent developing them. -
Do chronic wounds need to be dressed daily?
Jan 11, 23 02:18 PM
Because of supply chain shortages as well as staffing shortages particularly during the pandemic, many institutions extended the time between dressing changes for chronic wounds. Is this really the be… -
Food choices that raise your risk of type 2 diabetes
Jan 08, 23 10:07 AM
A good review of how blood sugars can become elevated and the harm that can do. Certain food groups have a tendency to raise your blood sugars and should be avoided. -
Outcome stats from Scarf bunionectomy
Jan 03, 23 03:04 PM
The Journal of Foot and Ankle Surgery recently reported a meta analysis of outcomes in 1583 Scarf bunionectomies that met their inclusion criteria. Adverse events did not seem to be any better or wors…