- Home
- juvenile bunions
juvenile bunions
• Juvenile bunions are bunion deformities that develop in children and teenagers, most often due to excessive pronation and hypermobility in the foot. This excessive motion causes the first metatarsal to drift inward while the big toe drifts outward, creating the bunion bump and abnormal joint alignment.
• A key feature is **metatarsus primus varus**, where the angle between the first and second metatarsals becomes abnormally large. X‑rays often show the first metatarsal shifting away from the others and the lateral sesamoid bone displaced, confirming long‑standing structural change.
• Many juvenile bunions are painless, but even painless deformities can worsen over time. When pain is present, it is often due to shoe pressure or early cartilage wear from the misaligned joint.
• Conservative care focuses on controlling hypermobility with orthotics, improving joint alignment, and slowing progression. Orthotics must be worn consistently—similar to eyeglasses—to be effective. Shoe modifications and occasional anti‑inflammatory medication may help with mild discomfort.
• Surgery is reserved for severe, painful cases that fail conservative care. Procedures often require correcting the metatarsus primus varus through osteotomy or fusion, and recurrence rates are higher than in adult bunion surgery. Surgery cannot be performed until growth plates are closed.
Reviewed by: Medical Review Board
WHAT ARE JUVENILE BUNIONS
As the name implies, it is a bunion deformity that occurs in children, generally teenagers. Most people associate bunion deformity with a condition that occurs in older individuals. By and large that is true in that most bunion deformities occur in older individuals and tend to be a long progressive deformity that eventually reaches the point where it begins to hurt.
In bunions developing in children, the patient generally exhibits a hypermobile or flatfoot deformity where there is too much pronation which creates excessive motion in the foot and results in a splaying or spreading of the metatarsals. See the anatomy page.
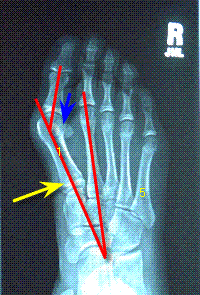
Seen in most cases of juvenile bunions is a metatarsus primus varus where the first metatarsal bone is much further from the second metatarsal compared to the relationship of the second, third, fourth and fifth metatarsal bones. In the x-ray pictured below look at the two larger red lines that form a “V”. Notice the angle formed is much larger than any other angle between the other metatarsal bones.
|
This enlarged angle has forced the first metatarsal bone to “move away” from the other metatarsal bones as a result of the hypermobility exhibited by the patient. As the first metatarsal bone moves in one direction, the big toe begins to move in the opposite direction toward the second toe and what you end up with is a protrusion on the inside of the foot that is subject to excessive shoe pressure but probably even more important, an abnormal alignment between the big toe and the first metatarsal. This abnormal alignment will result in a premature erosion of the cartilage of this joint and then ultimately pain.
Looking at the x-ray again, you will notice the blue arrow pointing to a small round bone. This is known as the lateral sesamoid bone and in a normal structured foot this bone actually lies directly underneath the first metatarsal bone. This is further proof to us that the first metatarsal bone has actually moved over the passage of time.
TREATMENT OF JUVENILE BUNIONS
conservative care
OK, so now we are all experts on juvenile bunions; what are we going to do about them?
Although unsightly, in many cases they are painless deformities. In those situations our goal is to try and prevent them from getting worse. In order to accomplish that we have to control the hypermobility, that I mentioned earlier. If we can control the excessive motion occurring in the foot we can cut down on the forces that are aggravating and causing the bunion to form. We accomplish that through the use of orthotics.
Not only do we cut down on the hypermobility but we also create better alignment of the joint in an effort to cut down on the erosion of the joint.
There are a few things worth mentioning about orthotics as it relates to the juvenile bunion.
1. If the child has not finished growing, he or she is probably going to out-grow the orthotics in less than two years, which will require a new pair. It is fairly safe to say that the patient will require orthotics throughout their adult life as the tendency for hypermobility exists even in adulthood.
2. To get the maximum amount of good out of an orthotic the patient has to wear them as much as possible. A scenario where the child wears them all day at school, then comes home and takes off their shoes and runs around barefoot for another 6-7 hours kind of defeats the whole purpose.
As soon as you remove the orthotic the foot returns to its normal position of hypermobility and the forces that are aggravating the bunion formation are back in play. Orthotics work like eyeglasses; when you wear them they do the job that they are intended to do, when you remove them everything reverts back to the way it was. Click the image to the left to learn more about orthotics for juvenile bunions.
3. Unfortunately, not all juvenile bunions are painless. In the instances where there is a small amount of discomfort, orthotics and modification of the type of shoe worn by the patient may help alleviate the pain. For occasional pain, Advil or Aleve taken short-term can be very helpful.
I am constantly being asked if there are exercises you can do to strengthen the foot to get rid of the bunion and the answer is NO. Rolling a ball under your arch will not strengthen it or keep it from flattening out.
surgical correction
In those situations where conservative measures have failed you have to consider surgical intervention. The problem here is that you are having a procedure done that has a relatively high failure rate.
I have seen statistics stating a failure rate of 60 percent. Even if the initial procedure is successful you are now hoping that the procedure will last the next 60-70 years; a probability I find to be quite low. So, even with a successful procedure there is a relatively high probability that the patient may need additional surgery somewhere “down the road”.
To further complicate the situation most juvenile bunions cannot be corrected with simple bunionectomies where just the enlarged “bump” is removed. The issue of the metatarsus primus varus has to be addressed in order to get better alignment of the big toe joint.
To accomplish this, depending on how bad the deformity is, either an osteotomy (the surgical breaking and realigning of bone) will have to be performed or a fusion of the base of the first metatarsal to the bone behind it (cuneiform bone) will be necessary in order to stabilize the first metatarsal.
Although I have no firsthand experience, there is a relatively new procedure out known as a partial epiphysiodesis. In this procedure a bone staple is inserted into the first metatarsal bone in the area of the growth plate (see the yellow arrow in the xray) in an effort to redirect the growth of the metatarsal bone back in the direction of normal alignment.
The problem here is that it can only be done at a certain stage of bone development, the growth plate still being widely open. Which would mean that at that point the child is probably not having any subjective pain and may or may not even notice the bulge that is developing on the inside of the foot. Because of these limitations to the procedure there would not be many candidates out there. I do suspect, however, that it is a minimally traumatic procedure and in the right situation could be a very rewarding surgery.
The right choice may not be easy to come by. My feeling is that surgical intervention should be considered only on juvenile bunion deformities that hurt a lot on a regular basis. These are bunions that have not responded at all to conservative care. I talk to my patients all the time about “risk vs. reward”.
After all is said and done this is elective surgery, so one has to weigh the possible reward (resolution of pain) with the possible risks (infection, surgical failure, surgical success with a second procedure later on in life, among others). The only way the “risk vs. reward” ratio works in your favor is if you are in so much pain that the juvenile bunion deformity is adversely affecting your ability to do the things you want to do on a daily basis.
It should also be noted that no matter how much pain the child may be in, the procedure cannot be performed until their growth plates are closed and the bones are finished growing. Once again look at the x-ray and notice the yellow arrow; it is pointing to the growth plate of the first metatarsal which in this case is still open.
Although a second opinion is always indicated prior to surgery, I think this is one situation where it should be mandatory.
Frequently Asked Questions
REFERENCES
If you happen to live in the New York - New Jersey area and would like to visit our office
|
|
To make an appointment online or for directions to our office click Dr. Marc Mitnick.
DISCLAIMER: The purpose of this site is purely informational in nature. It is not intended to diagnose, treat or cure any medical condition. This information is not a substitute for advice from a medical professional. Please consult your healthcare provider for accurate diagnosis and treatment. The information presented here may be subject to errors and omissions.
SITE LAST UPDATED: October 2026

Recent Articles


-
Vitamin D impact on health
Feb 06, 23 07:17 PM
Researchers are suggesting that the effectiveness of Vitamin D in fighting and preventing disease is predicated on a persons body mass index (BMI). The thinner the person the greater the positive impa… -
Foods to speed up healing
Feb 01, 23 02:41 PM
One of the best ways to help yourself heal faster after surgery is to eat well. Getting the proper nutrition will provide your body with the essentials it needs to promote healing. Here is a suggestio… -
Cancer and Type 2 Diabetes
Jan 25, 23 04:52 PM
An article revealing that older type 2 diabetics have a higher incidence of cancer then non-diabetics. It is suggested that cancer may surpass CVD as the number one cause of death in older diabetics. -
Does glucosamine or MSM reduce arthritis pain?
Jan 22, 23 01:41 PM
A good review of the possible benefits to taking glucosamine, chondroitin or MSM for arthritis. Always beware of the possible side effects of over the counter supplements. -
shin splints
Jan 18, 23 05:12 PM
A great review on the various causes of shin splints, along with treatment options. -
Whats new in skin cancer?
Jan 15, 23 08:32 PM
A presentation of newer skin protection combinations in an effort to better protect the skin from the hazards of sun exposure. -
Causes and risk factors of warts
Jan 14, 23 05:02 PM
A good review of the causes of warts and protective measures you can take to prevent developing them. -
Do chronic wounds need to be dressed daily?
Jan 11, 23 02:18 PM
Because of supply chain shortages as well as staffing shortages particularly during the pandemic, many institutions extended the time between dressing changes for chronic wounds. Is this really the be… -
Food choices that raise your risk of type 2 diabetes
Jan 08, 23 10:07 AM
A good review of how blood sugars can become elevated and the harm that can do. Certain food groups have a tendency to raise your blood sugars and should be avoided. -
Outcome stats from Scarf bunionectomy
Jan 03, 23 03:04 PM
The Journal of Foot and Ankle Surgery recently reported a meta analysis of outcomes in 1583 Scarf bunionectomies that met their inclusion criteria. Adverse events did not seem to be any better or wors…