- Home
- wound care
wound care
Foot wounds are uniquely challenging to heal because circulation is often compromised and every step places pressure directly onto the injured tissue, slowing recovery. This combination makes the foot one of the most common—and most difficult—locations for chronic wounds, requiring specialized care and strict off‑loading to prevent deterioration.
Modern wound care relies on a team approach, but podiatrists typically manage the day‑to‑day treatment. Healing can be slow, and some wounds may never fully close, especially when complicated by diabetes, neuropathy, poor circulation, excess pressure, or improper footwear. Consistent off‑loading is critical; walking on a plantar wound dramatically delays healing and increases the risk of infection or limb loss.
Treatment varies because no two wounds are alike. Care may include debridement, moisture‑balancing dressings, infection control, and pressure reduction through casts, boots, or crutches. Dressings are selected based on drainage level and wound characteristics—ranging from calcium alginates for heavy drainage to hydrogels for dry wounds. Regular monitoring of wound size, depth, tissue quality, and surrounding skin guides adjustments in therapy.
Reviewed by: Medical Review Board
Within the last 20 years or so, wound care has become a specialty all onto itself. I do not have any hard facts to support the following statement, but the foot probably demonstrates the highest incidence of wounds more so than any other part of the body.
Additionally, the foot has obstacles in treating wounds that is not seen elsewhere in the body. The two most obvious obstacles are the fact that circulation to the foot in many cases is compromised and by walking on the foot (and the wound), the healing process is greatly diminished.
Podiatrists have become the leaders in the local management of wounds. Most wound care is done in a team approach, meaning other medical specialties get involved, but the day to day care of the wound falls in the hands of the podiatrist.
For those who suffer from wounds of the foot the healing process can end up being a long drawn out process; in some cases a wound never heals and with a chronic wound the patient is always at risk for infection and loss of limb. Wound care in the foot is a complicated procedure, there is no one approach. Each wound is different and requires different treatment.
The purpose of this article is to help those who are presently suffering from a wound of the foot in understanding the wound care process. Hopefully, what you read here will reinforce what your doctor has told you and you as the patient, will be more compliant in the instructions you have already been given.
can I walk on my foot wound?
|
There is no two ways about it, a wound on the bottom of the foot is going to adversely affect your every day lifestyle. The gold standard for off-loading a wound is through the use of a contact cast. Sometimes cam walkers may be used along with special surgical shoes and in some cases your doctor will just want you using crutches. The decision as to what type of off-loading to employ is based on a few factors including location of wound, weight of the patient, physical capabilities of the patient, etc.
For those of you who are suffering from a wound on the bottom of your foot, you probably noticed that prior to the wound you may have had a callus or hard spot in the area that the wound now occupies. What happens is due to too much pressure on an underlying bone, the body will normally form a callus in varying thickness.
The thickness will be determined by the overall foot structure of the patient, their overall body weight, the types of shoes they wear and the walking surfaces where they do the most walking. All things being equal, a letter carrier would stand a greater chance of developing a foot wound than someone who sits at a desk all day.
factors that contribute to wounds on the bottom of the foot
Due to a lot of variables such as:
- lack of sensation on the bottom of the foot
- poor circulation to the foot
- elevated blood sugars in an uncontrolled diabetic
- poor foot hygiene
- improper shoes
- excess body weight
|
As I mentioned earlier, not all wounds are the same and so wound care will differ from person to person. For this reason the medication used for wound care will also vary from patient to patient. There is no one topical medication that is effective for all types of wounds. The purpose of these different types of dressing is to create an optimum environment for wound healing to take place.
four categories of wound care dressings
calcium alginates- The first group is known as the calcium alginates. An example would be Silvercel which are very absorbent. Many wounds present with a lot of drainage. In order to create the optimum environment, the wound has to be dried out to some extent, and Silvercel will absorb the moisture to form a gel. This type of dressing is changed frequently and is used until the wound is much less moist but not completely dried out.
foams- The next classification of dressing are known as foams. They too are used to treat heavy draining wounds and the nice thing about this type of dressing is that they will not stick to the wound and can be left on longer than the calcium alginates. An example of the foams is Polymem.
collagens- The next group are known as the collagens which are also absorbent and will not stick to the wound. In addition to pads they also come in powders. They can be packed into the wound and are used for infected wounds. A point to be made here is that all infected wounds will have drainage, but not all draining wounds are infected.
That is an important distinction and that will explain why some patients are put on antibiotics either oral or intravenous and other are not put on antibiotics. An infected wound will have certain characteristics and in this day and age it is important to avoid the indiscriminate use of antibiotics which in the long run lessen the effectiveness of antibiotics in general.
|
Again, it is all about creating the optimum wound environment, which is a moist wound that is not draining. Years ago betadine was the standard for treating wounds and while betadine is great at killing bacteria it dries the wound out so much that there is virtually little chance of the wound closing. Betadine still has a place in wound care and it is usually used when the patient first presents with a heavy draining wound, but once the wound shows signs of reduced draining, the dressing should be switched to another type dressing.
With all the above dressings the frequency with which they are changed will vary from patient to patient and is based on what your doctor is trying to accomplish. A dressing that has a tremendous amount of drainage, may initially have to be changed daily until the drainage diminishes at which point the dressing change will be less frequent.
evaluating your wound
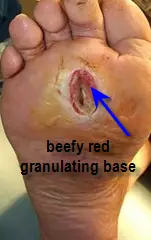
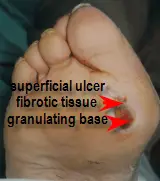
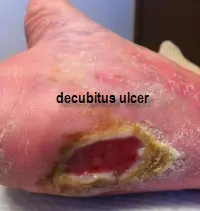
During your visit to the podiatrist, he or she will generally first observe the wound. The things that are important to note include the diameter of the wound and the depth of the wound and usually your doctor will measure these at each visit. Obviously a reduction in width and depth shows that the wound is improving. The doctor will also note what the base or bottom of the wound looks like.
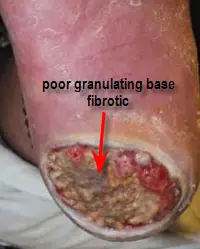
A good healthy wound with adequate blood coming into the area should appear beefy red. This is known as a good granulating base meaning all the components are in place for healing. Sometimes, however, the base of the wound will be greyish to yellow in color and this is a sign of a poor granulating base and thus the chances of closure are dramatically reduced.
|
Your doctor will also make note of the edges of the wound. In many instances the tissue around the wound becomes very hard. Again, the more you bear weight on the foot, the harder the surrounding skin will become. The problem here is that this skin which is known necrotic skin not only makes closure of the wound difficult but it is a focal point for bacterial infection.
Once your doctor is done observing the wound, he or she will usually debride (cut away) all this necrotic tissue in an effort to once again create an optimum wound healing environment. Depending on the type of wound, most of them can be debrided in an office environment, however, some wounds such as very dry ulcers may be too painful to debride and will have to be done in the hospital under sedation. As a side note, if there happens to be a lot of bleeding, that is actually a good thing as it demonstrates that adequate blood is coming into the wound.
What I have discussed so far is the basic management of wounds, at least on the foot. However, in many instances this may not be enough to get the wound to close. At this point, and this point being where your doctor has noted that there has not been any substantial improvement in the size of the wound over a month or two. The rule of thumb is if the ulcer size has not decreased by 50 percent in this period of time, then chances are it will never close without additional treatment approaches.
continue....wound care, advanced treatments
Frequently Asked Questions
REFERENCES
If you happen to live in the New York - New Jersey area and would like to visit our office
|
|
To make an appointment online or for directions to our office click Dr. Marc Mitnick.
DISCLAIMER: The purpose of this site is purely informational in nature. It is not intended to diagnose, treat or cure any medical condition. This information is not a substitute for advice from a medical professional. Please consult your healthcare provider for accurate diagnosis and treatment. The information presented here may be subject to errors and omissions.
SITE LAST UPDATED: October 2026

Recent Articles


-
Vitamin D impact on health
Feb 06, 23 07:17 PM
Researchers are suggesting that the effectiveness of Vitamin D in fighting and preventing disease is predicated on a persons body mass index (BMI). The thinner the person the greater the positive impa… -
Foods to speed up healing
Feb 01, 23 02:41 PM
One of the best ways to help yourself heal faster after surgery is to eat well. Getting the proper nutrition will provide your body with the essentials it needs to promote healing. Here is a suggestio… -
Cancer and Type 2 Diabetes
Jan 25, 23 04:52 PM
An article revealing that older type 2 diabetics have a higher incidence of cancer then non-diabetics. It is suggested that cancer may surpass CVD as the number one cause of death in older diabetics. -
Does glucosamine or MSM reduce arthritis pain?
Jan 22, 23 01:41 PM
A good review of the possible benefits to taking glucosamine, chondroitin or MSM for arthritis. Always beware of the possible side effects of over the counter supplements. -
shin splints
Jan 18, 23 05:12 PM
A great review on the various causes of shin splints, along with treatment options. -
Whats new in skin cancer?
Jan 15, 23 08:32 PM
A presentation of newer skin protection combinations in an effort to better protect the skin from the hazards of sun exposure. -
Causes and risk factors of warts
Jan 14, 23 05:02 PM
A good review of the causes of warts and protective measures you can take to prevent developing them. -
Do chronic wounds need to be dressed daily?
Jan 11, 23 02:18 PM
Because of supply chain shortages as well as staffing shortages particularly during the pandemic, many institutions extended the time between dressing changes for chronic wounds. Is this really the be… -
Food choices that raise your risk of type 2 diabetes
Jan 08, 23 10:07 AM
A good review of how blood sugars can become elevated and the harm that can do. Certain food groups have a tendency to raise your blood sugars and should be avoided. -
Outcome stats from Scarf bunionectomy
Jan 03, 23 03:04 PM
The Journal of Foot and Ankle Surgery recently reported a meta analysis of outcomes in 1583 Scarf bunionectomies that met their inclusion criteria. Adverse events did not seem to be any better or wors…