- Home
- puncture wounds
puncture wounds (and foreign bodies)
Puncture wounds occur when a sharp object penetrates the skin, and in the foot they carry a higher risk of infection and hidden injury. Even when the object is removed, complications can develop—especially if treatment is delayed or if the patient has diabetes, poor circulation, or a weakened immune system.
These injuries vary widely. Some people feel immediate pain, while others barely notice the puncture, particularly those with neuropathy. Foreign bodies such as wood, glass, or metal may remain embedded, and walking can push them deeper into the foot. X‑rays can detect many objects, while ultrasound or MRI may be needed for materials not visible on X‑ray.
Infections are a major concern. Bacteria such as Pseudomonas aeruginosa, MRSA, and Clostridium tetani (tetanus) are associated with puncture wounds, especially those involving dirty or contaminated objects. Not all wounds require antibiotics, but signs such as redness, swelling, drainage, or increasing pain warrant medical evaluation.
Tetanus protection depends on the patient’s immunization history. Deep or contaminated wounds may require a booster. Deeply embedded foreign bodies or those near joints, nerves, or blood vessels may need removal under anesthesia to prevent further damage.
Reviewed by: Medical Review Board
A puncture wound is a break that occurs in the skin from a foreign object. The foreign object may or may not stay embedded in the skin and structures below the skin. A wound of this nature may occur anywhere on the body but as you can well imagine is very common in the foot. This discussion will relate to punctures of the foot.
Assuming the foreign object is removed, most wounds will heal uneventfully, but a certain percent who delay medical care will develop complications, primarily an infection. More severe complications include osteomyelitis which is a bone infection, a septic joint (infected joint) from penetration of the foreign body into a joint, neurological impairment due to damage to a nerve, or vascular impairment as a result of the foreign body damaging a blood vessel, and loss of function in a certain area due to the penetrating trauma inflicted by the foreign body.
This type of wounds are very common in children, people who work outdoors, at construction sites, and people who do a lot of walking in bare feet.
Initially, the presentation of a puncture wound will vary widely between patients. Some people will know they stepped on something, may or may not been able to remove the object, and have no pain. Others will have trouble walking even though they have no overt sign of infection and of course others will have difficulty walking and their foot will be red and swollen.
who is at greater risk with a puncture wound
In addition to the wound, a person’s medical history comes into play as it relates to wounds of the foot. For example, a poorly controlled diabetic or a patient with poor circulation to the foot is at greater risk for infection. One of the problems with a diabetic is that they may not know they stepped on a foreign object because of diabetic neuropathy, or the inability to feel the bottom of their feet.
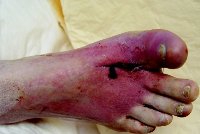
People with immunosuppressive diseases are also at greater risk for infection and exacerbated problems from a puncture wound. The picture below is that of a puncture wound in between the first and second toe in a diabetic.
|
Pinpointing the wound is usually easy enough but determining the presence of a foreign body in some cases can be very difficult. In superficial wounds like splinters and broken glass, the foreign body is either protruding from the skin or is just below the outer layer of skin. These wounds are easy to clean. Problems may occur when either the patient has tried to remove the foreign body, may or may not had success, but then comes in and the foreign body has been pushed further into the foot, or the partial remnant left over is more difficult to reach.
Additionally, in many cases the patient has been walking around with the foreign body in their foot for days and the pressure of walking has pushed the foreign object further into the foot. Depending on the mechanism of injury sometimes the foreign object is fairly far away from the actual site of the puncture wound.
removal of a foreign body
Knowing where the foreign object is located and how deep it is goes a long way in determining how difficult it will be to remove. Most superficial foreign bodies can be removed in the office, many without anesthesia. The problem arises when it is determined that the foreign object is too deep and to remove it will require a fair amount of dissection. These cases are better treated in the hospital under anesthesia and adequate hemostasis (control of bleeding).
When the foreign body is determined to be deeper in the foot there are a number of diagnostic tests that can be performed to determine the location. The simplest is an x-ray with at least two views. X-rays will spot any metallic objects like nails or pins and even glass depending on the lead content of the glass.
For more difficult objects not seen on x-ray an ultrasound or MRI may be indicated. MRI’s are particularly helpful in not only identifying a foreign body, but also for checking to see if there has been any structural disturbance.
antibiotics for puncture wounds
In evaluating a foreign body it is important for the doctor to know the type of material that penetrated the foot and where the accident occurred. A piece of metal from a dirty construction site carries a greater chance of infection then a sewing needle stepped on at home.
Not all wounds require antibiotics. Right now there are no significant studies that suggest routine administration of antibiotics for the prevention of infection in foreign bodies will actually improve outcomes. The decision for antibiotics rests with your doctor. If your wound shows signs of infection like drainage, swelling, redness and pain you are probably a candidate for an antibiotic. Duration of the antibiotic will also be at the discretion of your doctor.
Two common organisms found in puncture wounds are Pseudomonas aeruginosa and methicillin resistant Staph aureus (MRSA). Although most infections do not end up in osteomyelitis, when it does it is usually a Pseudomonas infection. When a puncture wound fails to heal MRSA has to be ruled out.
The organism most associated with puncture wounds is Clostridium tetani which is associated with tetanus.
tetanus and puncture wounds
What about tetanus immunization? Generally, clean minor wounds do not require tetanus innoculation. Wounds that are contaminated with dirt, feces or are deep penetrating wounds may require a tetanus shot depending on the patient’s tetanus history.
If you are uncertain or have had less than 3 doses of Td (adult tetanus and diphtheria toxoids) or TIG (tetanus immune globulin) you will probably require immunization. If you have had your three doses but they were over five years ago, then you too will require additional immunization.
Frequently Asked Questions
REFERENCES
Questions I Have Answered From Visitors
Broken sewing needle in foot with continued throbbing pain
Visitor's question
I had an X-ray done to confirm that there is a broken sewing needle in my foot. There was — between the toes, slanting downward. An antibiotic was prescribed (Keflex) and I was told to soak the foot in warm water and that it might come out on its own.
I’ve finished the antibiotics. There is less puffiness of the toes, and I soak my foot in warm water with Epsom salts. I’m still experiencing some throbbing, but not constant. I’m on my feet 8–12 hours a day (I work in an emergency room). Now there is a black‑bluish lump.
Should I be worried? The staff physicians suggest I think it over before having it dug out and that I should try to live with it.
Doctor's answer
Hi,
Up to this point you have not really gotten very good advice. If the sewing needle is lodged in the foot, there is almost no way it is coming out on its own. You can soak your foot for a year and the only way the needle will come out from soaking is if it is partially exposed. If it is partially exposed, it can be removed manually.
So what are your options?
Depending on how big the embedded piece of needle is, they have been known to burrow backwards and deeper into the tissue (much more commonly than coming out). In many cases, if they burrow deep enough and are not hitting any structures like a tendon or nerve, there is a chance they may eventually stop hurting.
The other option, of course, is to have it removed. Depending on the experience of the doctor dealing with the problem, sometimes they can be removed in a setting like an emergency room, but more than likely they will have to be removed in the operating room.
You know the old saying “it’s like looking for a needle in a haystack”? Well, sometimes removing a needle can be almost as difficult.
Many times, just opening up the original entry site where the needle penetrated and lightly probing the area allows the needle to be felt and removed. If that does not work, the needle can be identified under ultrasound and then removed.
I have not seen your X‑ray, nor do I know how long the needle is, but if the needle is angled, more than likely if it were to get pushed back, it would hit one of the toe bones or the head of the metatarsal, preventing it from migrating further.
The fact of the matter is: if the needle hurts, then it has to be removed — it is just that simple.
One caveat: you mention a black‑and‑blue lump. If that lump is at the spot where the needle entered the foot, you may be developing a sterile abscess — the body’s way of walling off the foreign body. The good news is that if you have developed an abscess, a doctor can carefully open it, and in many instances the head of the needle will be sitting right there and can be easily removed.
Marc Mitnick DPM
Extreme sharp pain in my big toe
Visitor's question
Quite simple cause really.
In November, I stepped on a drawing pin which went all the way into my big toe. I immediately pulled it out (no blood) and went to bed (was hurting). Over the next week it hurt when I put my full weight on it but eventually the pain went away.
Now here's the strange bit.
Now and then when I walk on it again I get EXACTLY the same pain as if I am stepping on it again. The pain goes away quickly but just for a few moments it is extremely painful (sharp). There is no sign of infection or anything.
I am an ex semi-pro rugby player so I know what pain is, so I am not making a mountain out of a mole hill, as they say.
It is now February and I am completely bemused why I am still getting this.
I have had tetanus and apart from some fungi on my feet everything else is fine.
Best regards,
Darren
Doctor's answer
Hi Darren,
Strange things happen all the time, but I am not so sure this is one of them. Evidently, when you stepped on the pin, it did some damage to a structure in your toe.
I will assume the pin went into the bottom of your toe (you stepped on it), and if that is the case and if the pin entered exactly in the middle portion of the bottom of the toe, then my first thought would be that you may have done some damage to the flexor tendon, which is the tendon that allows you to bend your toe downward.
If the pin insertion was off‑center, then the pin may have hit the bone. If the pin insertion was more to the outside of the toe, then there is always the possibility that the pin hit what is known as one of the proper digital nerves, which are nerves that go into the toe and give you sensation.
So now the question becomes how much force was exerted when the pin went through the skin and “stuck” whatever structure it hit. The point of all this is that you probably aggravated something just enough that it flares up from time to time, and when it does flare up it hurts for a short period of time.
Without having the luxury of being able to see where the pin actually went into your toe, it is impossible for me to be any more specific.
You certainly could visit a local doctor and have him or her examine you to help determine what structure was damaged. The biggest concern on my part is that perhaps you did hit the bone. In these cases there is always the concern of a bone infection (osteomyelitis). Based on your narrative it does not sound like this occurred, but again, I cannot examine you.
So assuming there is no bone infection, here is what you can do. If you notice the incidence of pain is becoming less frequent and the intensity of each episode is getting weaker, then I would just wait it out and over time it should subside altogether. The problem is that because it is the bottom of your toe and you are constantly walking on it, the everyday walking will prolong the symptoms — unlike, for example, if you had stuck your finger with a pin; you could rest the finger and it would heal in a much quicker time frame.
On the other hand, if the intensity of the pain concerns you, then the logical choice would be to consult a local doctor.
Marc Mitnick DPM
If you happen to live in the New York - New Jersey area and would like to visit our office
|
|
To make an appointment online or for directions to our office click Dr. Marc Mitnick.
DISCLAIMER: The purpose of this site is purely informational in nature. It is not intended to diagnose, treat or cure any medical condition. This information is not a substitute for advice from a medical professional. Please consult your healthcare provider for accurate diagnosis and treatment. The information presented here may be subject to errors and omissions.
SITE LAST UPDATED: October 2026

Recent Articles


-
Vitamin D impact on health
Feb 06, 23 07:17 PM
Researchers are suggesting that the effectiveness of Vitamin D in fighting and preventing disease is predicated on a persons body mass index (BMI). The thinner the person the greater the positive impa… -
Foods to speed up healing
Feb 01, 23 02:41 PM
One of the best ways to help yourself heal faster after surgery is to eat well. Getting the proper nutrition will provide your body with the essentials it needs to promote healing. Here is a suggestio… -
Cancer and Type 2 Diabetes
Jan 25, 23 04:52 PM
An article revealing that older type 2 diabetics have a higher incidence of cancer then non-diabetics. It is suggested that cancer may surpass CVD as the number one cause of death in older diabetics. -
Does glucosamine or MSM reduce arthritis pain?
Jan 22, 23 01:41 PM
A good review of the possible benefits to taking glucosamine, chondroitin or MSM for arthritis. Always beware of the possible side effects of over the counter supplements. -
shin splints
Jan 18, 23 05:12 PM
A great review on the various causes of shin splints, along with treatment options. -
Whats new in skin cancer?
Jan 15, 23 08:32 PM
A presentation of newer skin protection combinations in an effort to better protect the skin from the hazards of sun exposure. -
Causes and risk factors of warts
Jan 14, 23 05:02 PM
A good review of the causes of warts and protective measures you can take to prevent developing them. -
Do chronic wounds need to be dressed daily?
Jan 11, 23 02:18 PM
Because of supply chain shortages as well as staffing shortages particularly during the pandemic, many institutions extended the time between dressing changes for chronic wounds. Is this really the be… -
Food choices that raise your risk of type 2 diabetes
Jan 08, 23 10:07 AM
A good review of how blood sugars can become elevated and the harm that can do. Certain food groups have a tendency to raise your blood sugars and should be avoided. -
Outcome stats from Scarf bunionectomy
Jan 03, 23 03:04 PM
The Journal of Foot and Ankle Surgery recently reported a meta analysis of outcomes in 1583 Scarf bunionectomies that met their inclusion criteria. Adverse events did not seem to be any better or wors…